
Key Takeaways
- Map out the actual days needed for detox, step-down care, and buffers before disclosing anything at work, so protected time is planned rather than improvised.
- FMLA protects treatment for a substance use disorder as a serious health condition, but not absences caused by active use — admission to a supervised program is the hinge 1.
- Stack FMLA for job protection, short-term disability for income replacement, and PTO to bridge waiting periods, so the paycheck keeps moving during leave.
- Three privacy layers — HIPAA, 42 CFR Part 2, and Oklahoma’s ODMHSAS Chapter 15 — shield treatment records and even the fact that you were a patient 4, 6.
- Use a narrow HR script that names a serious health condition, inpatient treatment, and dates without disclosing diagnosis, substance, or facility — the form is designed that way 7.
- Oklahoma requires medically supervised withdrawal management under a licensed physician and registered nurse, so a local admission meets a state-regulated clinical standard 5.
- If FMLA eligibility fails, ADA reasonable accommodation can still provide time off for treatment, with the same confidentiality protections around medical information 8, 7.
- Have one private provider conversation before contacting HR to verify benefits, confirm dates, and understand how the certification will be written to the narrow standard required 7.
The calendar problem: how many days you actually need, and how to protect them
Before anything else, you have a scheduling problem. Medical detox is not a vacation you can pretend to take, and it is not something you can quietly do over a long weekend. Stabilization, monitored withdrawal, and a safe handoff to the next level of care take real days on the calendar, and those days need to be protected before you tell anyone at work anything 9.
Start with the math, not the feelings. A typical inpatient medical detox runs several days to a bit over a week, depending on the substance, your history, and how your body responds to medication 10. Add a buffer at the front for admission and at the back for the step-down to outpatient or residential care. You are not planning a single event. You are planning a short block of protected time.
Here is the good news, and it is real. The federal leave system already contains three separate doors you can walk through, and they do different jobs. FMLA protects your position when treatment qualifies as a serious health condition 1, 2. Short-term disability, if your plan offers it, replaces some of your income. PTO and sick time cover the gap immediately. You do not have to pick one. You stack them.
The rest of this piece walks you through the sequence: what FMLA covers, how the paycheck keeps moving, what your employer is legally allowed to see, and how a discreet Oklahoma City admission actually gets scheduled. None of it is legal advice. All of it is the logistics no one explained to you.
What FMLA actually covers when the medical event is detox
Treatment counts as a serious health condition; active use does not
Here is the distinction that trips up almost everyone reading this quietly at their desk. The Family and Medical Leave Act protects treatment for a substance use disorder when it qualifies as a serious health condition. It does not protect absences caused by the substance use itself 1. Missing Monday because you were using over the weekend is not covered. Being admitted Monday to a medical detox program under the care of a licensed provider can be.
The Department of Labor says it plainly: treatment for substance abuse may be a serious health condition when it meets the regulatory criteria, but absence because of the employee’s use of the substance does not qualify for FMLA leave 1. That is the whole hinge. Once you cross from using to being a patient in a supervised program, the legal frame changes.
What counts as the qualifying treatment? Inpatient care at a treatment center for addiction is on the list, and so is the continuing outpatient care that follows, including counseling and medication follow-up under a licensed provider 2. That matters because your leave block is not just the days you are in the detox bed. It can extend to the step-down appointments that keep you stable afterward.
Read this part slowly if you are scared: the moment you are formally admitted, you are a patient receiving medical care. That is the door FMLA is built around, and it is the door you are walking through.
Eligibility basics your HR portal will check
Before you say a word to anyone, confirm three things quietly in your benefits portal or your employee handbook:
- Your employer generally needs to have at least 50 employees within 75 miles of your worksite.
- You generally need to have worked there at least 12 months.
- You generally need to have logged at least 1,250 hours in the last 12 months 11.
If all three are true, you are in the FMLA-eligible pool. If one is not, you are not automatically out of options — short-term disability, PTO, and ADA accommodation still exist, and we get to those later — but your protection playbook shifts.
One more piece your HR portal will confirm: FMLA gives you up to 12 workweeks of unpaid, job-protected leave in a 12-month period for a qualifying reason 11. A medical detox admission plus step-down care rarely uses more than a small fraction of that. You are not asking for 12 weeks. You are asking for the days you actually need.
If you are researching this for a spouse
Some of you are not reading this for yourself. You are reading it because someone you love is deteriorating, and you want to be with them when they finally say yes.
The Department of Labor is direct on this point: eligible employees may use FMLA leave to care for a spouse undergoing inpatient treatment for substance abuse 11. That means you can protect your own job to be present during admission, sit in on the family session, and handle the pieces at home while they stabilize. Same eligibility rules apply to you as would apply to them — 12 months on the job, 1,250 hours, covered employer.
You do not have to name the substance to your HR team. You have to establish that your spouse has a serious health condition requiring inpatient care and that you are their caregiver.
Stacking PTO, short-term disability, and FMLA so the paycheck does not stop
The fear underneath the leave question is usually financial. You are not just asking how to be gone. You are asking how to be gone without the direct deposit going quiet, without the family noticing, and without a benefits statement showing up in the mail that says something you cannot explain. That is a reasonable thing to plan around, and the plan is layered — not a single lever.
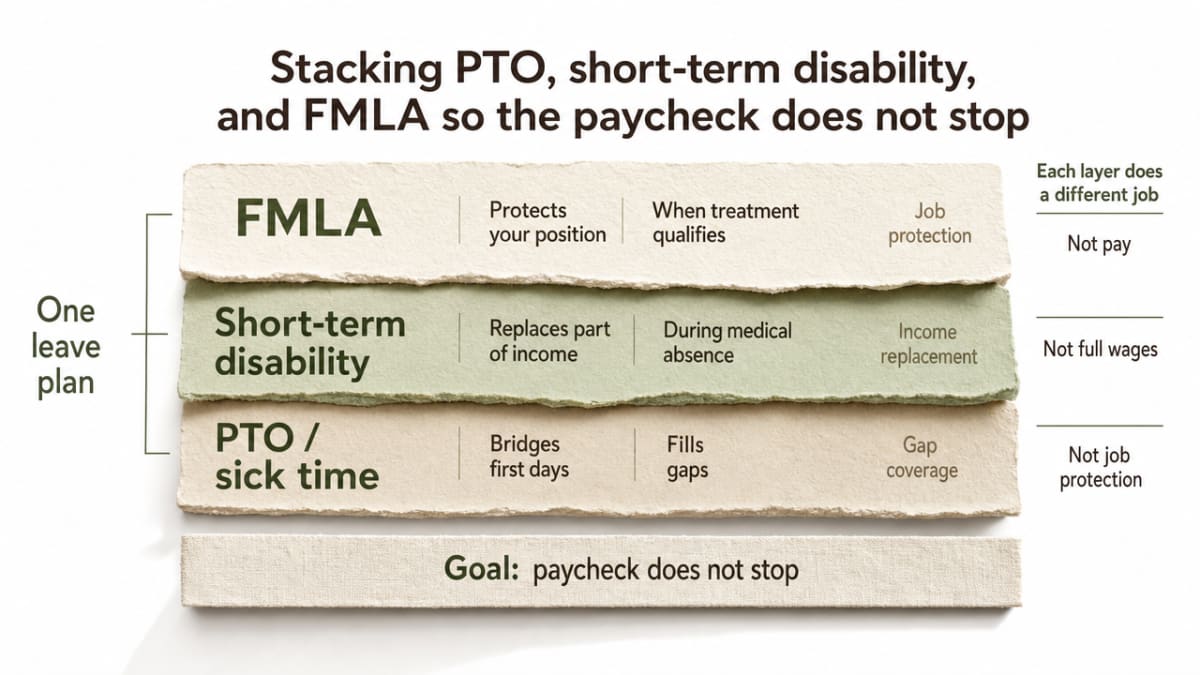
Think of your leave as three separate stacks doing three separate jobs:
- FMLA
- Protects your position when the treatment qualifies as a serious health condition, which inpatient care at a treatment center for addiction can 1, 2.
- Short-term disability
- If your employer offers it, replaces a share of your income during the medical absence.
- PTO and accrued sick time
- Bridge the first days and fill gaps the other two do not cover.
Run them at the same time when your plan allows it.
| Layer | What it does | What it does not do |
|---|---|---|
| FMLA | Protects your job and health benefits for up to 12 workweeks in a 12-month period when treatment meets the serious-health-condition standard, which can include inpatient care at a treatment center for addiction 1, 2. | Does not pay you. FMLA leave is unpaid on its own. |
| Short-term disability | Replaces a portion of your paycheck during a medically certified absence. Plan-dependent — the percentage, waiting period, and maximum duration are set by your employer’s policy. | Does not protect your job by itself. STD is an income product, not a leave law. |
| PTO and sick time | Immediate income from your accrued balance. Covers the STD waiting period and any days STD does not fully replace. | Runs out. Your employer sets the balance and the rules for how it stacks with FMLA. |
Here is how the stack usually plays out in practice:
- You apply for FMLA to lock in the job protection.
- You file the short-term disability claim with the same medical certification your provider prepares — the STD carrier sees the clinical detail, your employer does not 1.
- You use PTO to cover the STD elimination period, which is often the first week.
- When STD kicks in, PTO can top it up to full pay if your plan permits.
A few practical notes before you sit down with HR. Check your handbook for whether PTO runs concurrently with FMLA — many employers require it. Check whether your STD policy has a pre-existing condition clause and how it treats substance use disorders specifically, because that varies. And keep the medical certification your provider signs for FMLA separate in your head from the more detailed clinical paperwork the STD carrier will request. Different audiences, different levels of detail, same underlying treatment episode.
None of this is legal advice, and your benefits team can walk you through the exact interaction between your specific policies. What matters right now is that the paycheck does not have to stop for you to get admitted. The system already contains the mechanics.
The two federal privacy shields around a detox admission
HIPAA, 42 CFR Part 2, and the 2024 final rule
The fear that keeps you up at night is not really about withdrawal. It is about someone in your office finding out. That fear deserves a real answer, and the real answer is that your treatment records sit inside not one but three overlapping layers of privacy law, each doing a different job.
The outer layer is HIPAA. It covers medical information generally and sets the baseline rules about who can access, use, and disclose your health data. Your detox provider, your health plan, and anyone processing claims are bound by it. That is the shield you already know about from every doctor’s office paperwork you have ever signed.
The middle layer, and the one built specifically for you, is 42 CFR Part 2. It applies to records from federally assisted substance use disorder treatment programs, and it has always been stricter than HIPAA. Under Part 2, your records generally cannot be used in legal proceedings against you without your specific written consent or a court order 4. That is a protection HIPAA alone does not give you. If you have ever worried that a treatment record could resurface in a custody case, a licensing action, or a workplace investigation, this is the rule that stands between you and that outcome.
Part 2 got updated. HHS finalized a new rule in 2024 that aligns some Part 2 disclosures more closely with HIPAA to make coordinated care easier, while keeping the stronger patient protections in place; the compliance date is February 16, 2026 3. Practically, that means your records get treated more consistently across the health system, without losing the treatment-specific shield around them.
Three shields. Federal baseline, treatment-specific reinforcement, Oklahoma consumer-rights layer. None of them is a marketing promise. All of them are enforceable law.
What your employer is entitled to see on a medical certification
Here is the piece that quiets the loudest voice in your head: your employer does not get your chart. They get a certification form.
When you request FMLA leave, your employer can require a medical certification from your provider that confirms a serious health condition exists, states that leave is medically necessary, and gives an estimated duration. That is the level of detail the process is built around. The clinical narrative — the diagnosis, the substance, the facility name, the medications used during withdrawal — is not part of what HR is entitled to see.
The EEOC is clear about the guardrails on the other side of that form. All medical information an employer obtains must remain confidential, with only limited permitted disclosures — generally to supervisors and managers who need to know about work restrictions, to first-aid personnel when relevant, and to government officials investigating compliance 7. Your medical file is required to be kept separate from your regular personnel file.
What this looks like in practice: a certification that reads something like “patient has a serious health condition requiring inpatient treatment; leave estimated from [date] to [date]; will require follow-up outpatient care.” That is enough. Your provider knows how to write it that way. You do not have to coach them into vagueness — discretion is already the professional standard.
The takeaway is small and important. The form is narrow by design. Use it.
The HR conversation: a disclosure script that protects you
You do not owe your HR representative a story. You owe them the specific facts that trigger the leave process, and nothing else. That is not a loophole. That is how the form is designed to work.
Here is a script you can say out loud, or send in an email if that feels safer. Adjust the words to sound like you.
“I need to request medical leave for a serious health condition that requires inpatient treatment. My provider will submit the FMLA medical certification directly. I expect to be out approximately [date] through [date], with some follow-up outpatient care after. I would also like information on filing a short-term disability claim and how PTO coordinates with FMLA under our policy.”
Read what is in that script and what is not. You named a serious health condition. You named inpatient treatment. You named dates. You asked about the paycheck. You did not name a diagnosis, a substance, a facility, or a reason. That is the split the law is built around, and it is the split the EEOC guards on the other side — all medical information an employer obtains must remain confidential, with only limited permitted disclosures to supervisors handling work restrictions, first-aid personnel when relevant, or investigators 7.
A few tactical notes as you plan the conversation:
- Put the request in writing, even if you also say it in person, so the timeline is documented.
- Ask HR to send the FMLA certification packet directly to your provider — you do not need to be the messenger.
- If a manager pushes for detail out of curiosity or concern, redirect gently: “My provider is handling the medical documentation directly with HR.” That sentence closes the door without slamming it.
One more thing worth saying plainly. You are allowed to feel nervous walking into this meeting. Reading a script beforehand is not deception. It is preparation, the same as you would do for any other conversation that matters. The form is narrow on purpose. Use it, and let the paperwork do the talking your voice does not have to do.

How Oklahoma City detox admission actually gets scheduled
Withdrawal management under Oklahoma rules
You may have wondered, quietly, whether a local detox is actually medicine or just a rebranded rehab intake. The Oklahoma answer is written into state rule. ODMHSAS Chapter 18 requires that medically supervised withdrawal management be delivered under the direction of a licensed physician and a registered nurse 5. That is not a marketing claim about clinical quality. It is the floor the state sets before a program can be certified to admit you.
What that means on the ground is straightforward. When you are admitted, a licensed clinician evaluates you, sets a monitoring plan, and manages symptoms with medication when appropriate. For opioid withdrawal, that typically involves methadone, buprenorphine, or clonidine-based approaches; for alcohol, benzodiazepine-based management is standard 10. The goal of the first several days is stabilization and readiness for the next step, whether that is residential care or a structured outpatient program 9.
Understand what this does for your leave paperwork. When your provider signs a medical certification, they are certifying care that already meets a state-regulated clinical standard. HR does not see any of that clinical structure. They see a form. The medicine underneath the form is real, and the rules requiring it to be real are Oklahoma’s, not the facility’s.
A discretion-first local option and the Monday-admission pattern
Choosing a local Oklahoma City facility instead of a destination program out of state is a logistics decision as much as a clinical one. A local admission means shorter travel, easier coordination with your provider on the FMLA certification, and confidentiality that sits inside Oklahoma’s consumer-rights framework — where your identity as a patient is itself privileged and protected from release without written consent 6. That is a different posture than flying somewhere and leaving a longer paper trail behind you.
Renewal Springs Detox operates in Oklahoma City with that discretion-first posture built into how intake is handled. Benefits verification happens privately. The medical certification your employer sees is written to the narrow standard the form requires, not padded with clinical detail HR is not entitled to see 7. Your identity and clinical record stay inside the layered privacy shield already described.
The scheduling pattern most working professionals end up using looks like this:
- A Thursday or Friday intake call gets benefits verified and a bed reserved.
- The HR conversation happens Friday afternoon, using the disclosure script.
- Your provider transmits the certification directly to HR.
- You admit Monday morning.
By the time your team notices the out-of-office reply, the paperwork is already in motion — and the details are none of their business.
ADA accommodation as a backup when FMLA does not apply
What if you fail one of the FMLA eligibility tests? Maybe you have been at the job ten months, not twelve. Maybe the worksite has 40 employees, not 50. That does not close the door — it just changes which door you use.
The Americans with Disabilities Act treats substance use disorders differently from current illegal drug use, and the distinction is the same one FMLA draws. The EEOC has said that a person with alcoholism or a past drug addiction may be entitled to a reasonable accommodation, and that accommodation can include time off for treatment 8. Being in treatment moves you into protected territory. Being actively using does not.
What a reasonable accommodation looks like in practice depends on your role, but for a detox admission it usually means a defined block of unpaid leave, sometimes paired with a modified return-to-work schedule for follow-up appointments. You request it through HR, your provider supplies documentation that supports the need, and the employer engages in what is called the interactive process to work out the specifics.
The same confidentiality rules from the FMLA conversation apply here. All medical information your employer obtains must remain confidential and is kept separate from your personnel file 7. You disclose what triggers the accommodation — a medical condition requiring inpatient treatment and follow-up care — and nothing more. This is general information, not legal advice; a benefits attorney can confirm how ADA and any state parallel apply to your specific situation.
A private conversation, before you tell anyone else
You have read this far, which means the planning brain is already working. That is worth acknowledging. The decision to look up leave rules quietly, on your own time, is itself the first operational move — not the last one you have to make today.
Before you say anything to HR, before you fill out a single form, have one private conversation with a provider who can walk you through what an Oklahoma City admission actually looks like on your calendar. Verify benefits without a claim being filed. Ask how the medical certification gets written to the narrow standard the form requires 7. Ask what a Monday admission would mean for the specific week you are living inside right now.
Renewal Springs Detox takes that call privately. No commitment, no paperwork moving until you say so. One conversation, and then you decide what comes next.
Speak Privately About Medical Leave for Detox
Get confidential answers about taking leave for treatment without risking your privacy or job security.
Frequently Asked Questions
Can my employer find out I went to detox specifically, versus just knowing I was on medical leave?
No, not from the paperwork itself. Your FMLA certification confirms a serious health condition, medical necessity, and dates — not a diagnosis, facility name, or substance. All medical information your employer obtains must remain confidential and be kept separate from your personnel file 7. Your treatment records also sit under 42 CFR Part 2, which restricts disclosure of substance-use treatment records without your specific written consent 4.
How many days of leave should I plan for a medical detox admission?
Plan for roughly a week of inpatient stabilization and monitored withdrawal, plus a buffer for admission on the front end and step-down care on the back end. Actual length depends on the substance, your history, and how you respond to medication 10. SAMHSA guidance emphasizes stabilization and readiness for the next level of care, not a fixed clock 9. Ask your provider for an estimated date range before you talk to HR.
Does FMLA cover detox if I am still actively using right now?
The Department of Labor draws a hard line here. Treatment for substance abuse may qualify as a serious health condition when it meets the regulatory criteria, but absence caused by your use of the substance does not qualify for FMLA leave 1. Once you are formally admitted to a program under a licensed provider, you are a patient receiving medical care — and that is the door FMLA is built around 2.
What do I actually say to HR without disclosing that it is substance use?
Say you need leave for a serious health condition requiring inpatient treatment, that your provider will submit the FMLA medical certification directly, and give an estimated date range. Ask about short-term disability and how PTO coordinates with FMLA. That is enough. You are not required to name a diagnosis, facility, or substance, and the confidentiality rules on employer-held medical information limit what HR can share internally 7.
Will I get paid while I am out, or is FMLA leave unpaid?
FMLA itself is unpaid — it protects your job and health benefits, not your paycheck 1. Income comes from stacking. Short-term disability, if your employer offers it, replaces a portion of your wages during a medically certified absence. PTO and accrued sick time cover the STD waiting period and can top up partial payments. Many employers run PTO concurrently with FMLA, so check your handbook for how the layers interact.
Can my spouse take FMLA leave to be with me during inpatient detox?
Yes, if they meet FMLA eligibility. The Department of Labor confirms that eligible employees may use FMLA leave to care for a spouse undergoing inpatient treatment for substance abuse 11. Your spouse needs 12 months of tenure, at least 1,250 hours worked in the last year, and a covered employer. They do not have to name the substance to their HR team — only that you have a serious health condition requiring inpatient care.
References
- elaws – Family and Medical Leave Act Advisor. https://webapps.dol.gov/elaws/whd/fmla/10c9.aspx
- Fact Sheet #28O: Mental Health Conditions and the FMLA. https://www.dol.gov/agencies/whd/fact-sheets/28o-mental-health
- Understanding Confidentiality of Substance Use Disorder Patient Records. https://www.hhs.gov/hipaa/part-2/index.html
- Fact Sheet 42 CFR Part 2 Final Rule. https://www.hhs.gov/hipaa/for-professionals/regulatory-initiatives/fact-sheet-42-cfr-part-2-final-rule/index.html
- CHAPTER 18 – Oklahoma.gov. https://oklahoma.gov/content/dam/ok/en/odmhsas/documents/policy/provider-certification/administrative-rules/2023/PC–Chapter-18-Final-effective-9-15-23.pdf
- Chapter 15. Consumer Rights – Oklahoma.gov. https://oklahoma.gov/content/dam/ok/en/odmhsas/documents/policy/provider-certification/administrative-rules/2023/PC–Chapter-15-Final-effective-9-15-23.pdf
- Applying Performance and Conduct Standards to Employees with Disabilities. https://www.eeoc.gov/laws/guidance/applying-performance-and-conduct-standards-employees-disabilities
- The Mental Health Provider’s Role in a Client’s Request for Reasonable Accommodation at Work. https://www.eeoc.gov/laws/guidance/mental-health-providers-role-clients-request-reasonable-accommodation-work
- TIP 45 Detoxification and Substance Abuse Treatment. https://www.govinfo.gov/content/pkg/GOVPUB-HE20_400-PURL-gpo124442/pdf/GOVPUB-HE20_400-PURL-gpo124442.pdf
- Quick Guide For Clinicians Based on TIP 45 Detoxification and Substance Abuse Treatment. https://nida.nih.gov/sites/default/files/samhsa_detoxification_and_substance_abuse_treatment.pdf
- FMLA Frequently Asked Questions – U.S. Department of Labor. https://www.dol.gov/agencies/whd/fmla/faq


