
Key Takeaways
- Steady yourself before the conversation: write down specific behaviors you’ve witnessed rather than verdicts, because exhaustion and anger will overshadow the love underneath your words.
- Choose a private, sober moment and follow SAMHSA’s sequence: express concern, listen, offer concrete help, be patient, and keep the door open 1.
- Skip the hotel-room ambush. CRAFT training reshapes daily interactions and roughly triples treatment engagement compared with Al-Anon or Nar-Anon approaches 9, 6.
- Stop lecturing, lying for them, and issuing ultimatums you won’t keep, since these habits teach your loved one to tune you out.
- Build a safety floor now: keep naloxone in the house for opioid risk, and treat alcohol or benzo withdrawal as a medical situation needing supervision 12, 17.
- Know who to call before a crisis hits: 911 for medical emergencies like overdose, 988 for mental health or substance use crises, a detox line for urgent but non-emergency situations 18, 21.
- Treat detox as the on-ramp, not the destination. For opioid use disorder, pair it with buprenorphine, methadone, or naltrexone and ongoing counseling 16, 15.
- Keep going to therapy, meetings, and sleep even if your loved one refuses help, because you cannot flip a switch inside another adult and that limit is not your failure 10.
You’re Not Overreacting, and You’re Not Alone at This Table
It’s late. The dishes are still in the sink. You’re reading this on your phone because something happened again tonight, or last weekend, or every weekend for a while now, and you don’t know what you’re supposed to do next.
First thing: you’re not overreacting. If you’ve noticed your husband hiding bottles, or your daughter nodding off at dinner, or your brother burning through money nobody can account for, your gut is reading the room correctly. Families usually see it long before anyone else does. The fact that you typed “how to help a family member with addiction” into a search bar at this hour means you’ve already done the hardest part, which is admitting out loud that something is wrong.
Second thing: you’re not alone at this kitchen table. There is a federally recommended way to start the next conversation, a body of research on what actually helps someone accept treatment, and a real safety floor for the moments that feel dangerous 1, 2. This guide walks you through all of it in plain language, including what to say, what to stop saying, when to call 911 instead of 988, and when to pick up the phone and call us just to talk it through.
Before You Say Anything: Steady Yourself First
Here’s the part most advice skips: before you talk to them, you have to talk to yourself.
If you walk into this conversation shaking, angry about last Thanksgiving, or rehearsing a speech you’ve been writing in your head for six months, it will come out as an attack. Not because you’re a bad person. Because you’re a tired one. And they will hear the tired, not the love underneath it.
So give yourself an hour, or a day, or a weekend. Eat something. Call a friend who already knows. Write down, on paper, two or three specific things you’ve actually seen, not things you’ve assumed. “You missed Caleb’s birthday party and I found an empty bottle in the truck” is something you saw. “You’re throwing your life away” is a verdict. One opens a door. The other slams it.
It also helps to know, going in, that family involvement genuinely matters. Federal guidance on substance use treatment is clear that when family members engage thoughtfully, it can improve a loved one’s engagement, retention, and outcomes in care 4. You are not meddling. You are not making it worse by caring out loud. The research is on your side here.
And one more thing before you knock on that bedroom door. You are allowed to be scared. You can be scared and still be the person who starts this conversation. Those two things live in the same body all the time.
The Conversation: What to Actually Say
Pick the Moment, the Room, and the First Sentence
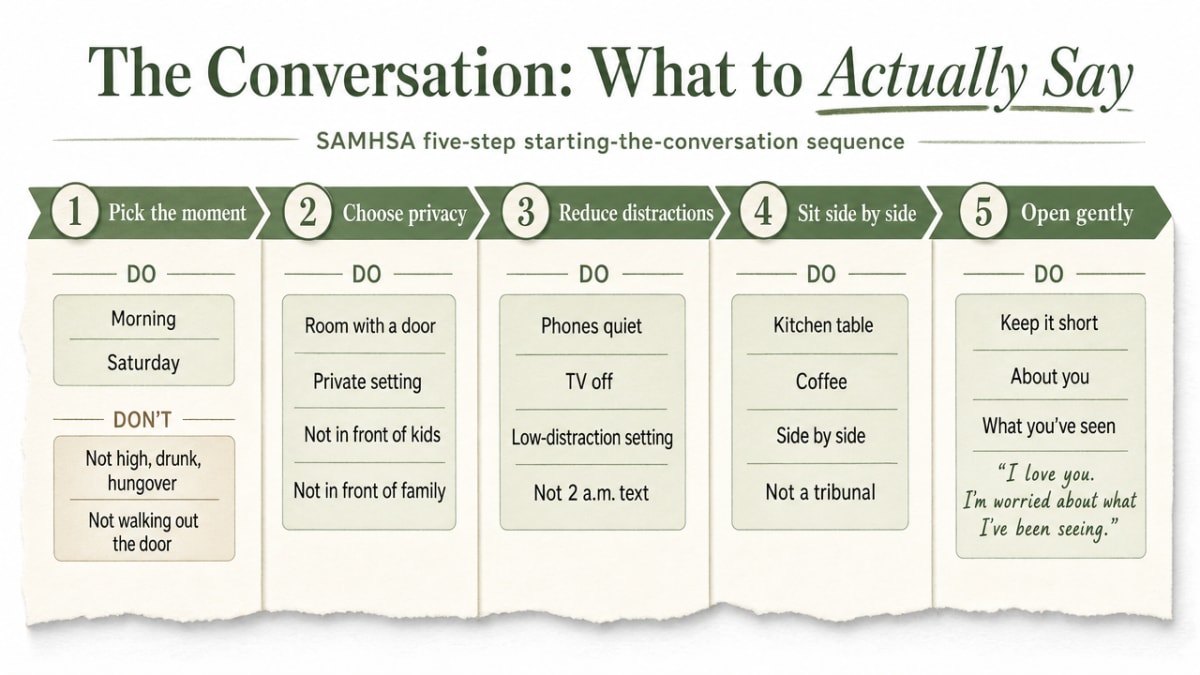
Timing matters more than you think. Don’t start this when they’re high, drunk, hungover, or walking out the door for work. Don’t start it in front of the kids, in front of your mother-in-law, or in a text message at 2 a.m. when you’re both exhausted and raw.
Pick a morning. A Saturday is usually better than a weeknight. Pick a room with a door that closes, where nobody’s phone is pinging and the TV is off. Federal guidance from SAMHSA is specific about this: a private, low-distraction setting changes how the conversation lands 1. Sitting side by side at the kitchen table, with coffee, often works better than facing them across the living room like it’s a tribunal.
Then the first sentence. Keep it short. Keep it about you and about what you’ve seen, not about what they are. Something like: “I love you, and I’m scared. I want to talk about what happened Friday night.” That’s it. You don’t need a speech. You need a doorway.
And then, this is the hard part, you stop talking and let them answer.
Say This, Not That: A Script You Can Borrow
If your mind goes blank the moment they look up, borrow this. SAMHSA’s starting-the-conversation sequence walks through five moves: express concern directly, acknowledge their feelings and listen, offer concrete help, be patient, and keep the door open 1. Here’s what each one sounds like at a real kitchen table.
Express concern directly. Say: “I noticed you’ve been drinking every night this week, and I found the bottle in the garage.” Not: “You have a problem and everyone knows it.” One is something you saw. The other is a label they’ll fight.
Acknowledge their feelings and listen. Say: “That sounds really hard. I didn’t know you were dealing with that.” Not: “Well, that’s no excuse.” You don’t have to agree with their reasons to hear them.
Offer concrete help. Say: “I’ll sit with you while you call. I’ll drive you. I already looked up a number we can try together.” Not: “You need to figure this out.” Vague help is no help.
Be patient. Say: “We don’t have to decide anything tonight.” Not: “If you don’t call tomorrow, I’m done.” Ultimatums close the door you just worked to open.
Keep the door open. Say: “Whenever you’re ready, I’m here. This offer doesn’t expire.” Not: “Fine. Forget I said anything.” You may be having this conversation more than once, and that’s normal, not failure.
When They Shut Down, Deflect, or Walk Out
They might cry. They might yell. They might tell you you’re the one with the problem, or bring up something you did in 2019, or just stand up and leave the room. Expect it. It doesn’t mean you did it wrong.
When they shut down, don’t fill the silence by escalating. Say, “Okay. I’ll be here when you want to talk,” and mean it. When they deflect onto your drinking, your spending, your mother, resist the urge to defend yourself for an hour. You can say, “We can talk about that too, and I want to. Right now I’m worried about you.”
When they walk out, let them. Don’t chase, don’t scream from the porch, don’t text seventeen times. SAMHSA’s family guide is clear that patience and a judgment-free posture matter more in the long run than winning any one conversation 2. Reopening the door tomorrow is a win. Getting them to a phone call next week is a bigger one.
You are planting something. It may not sprout the first time you say it out loud. That doesn’t mean nothing is growing.
Why CRAFT Beats the Ambush-Style Intervention
You’ve probably seen the TV version. Family members gather in a hotel conference room. The person walks in expecting lunch and gets handed a packed bag and a plane ticket to rehab. Cue the dramatic music.
Here’s the thing. That approach, usually called the Johnson Institute intervention, is not what the research actually recommends. There’s a quieter, less cinematic approach called CRAFT, short for Community Reinforcement and Family Training. It teaches you, the family member, how to reshape day-to-day interactions so that sober behavior gets reinforced and using behavior stops getting cushioned. No ambush. No ultimatum delivered by a stranger with a clipboard. Just a shift in how you respond, applied over weeks.
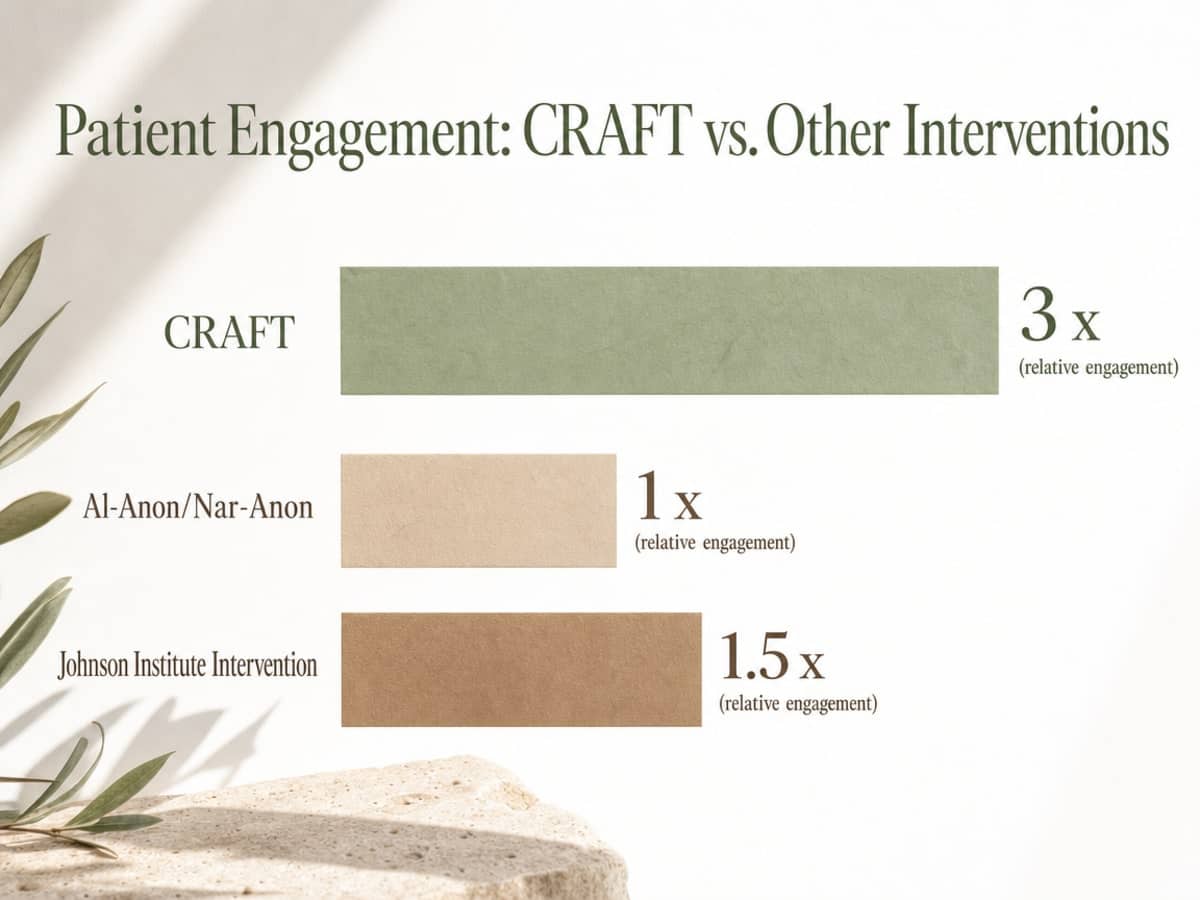
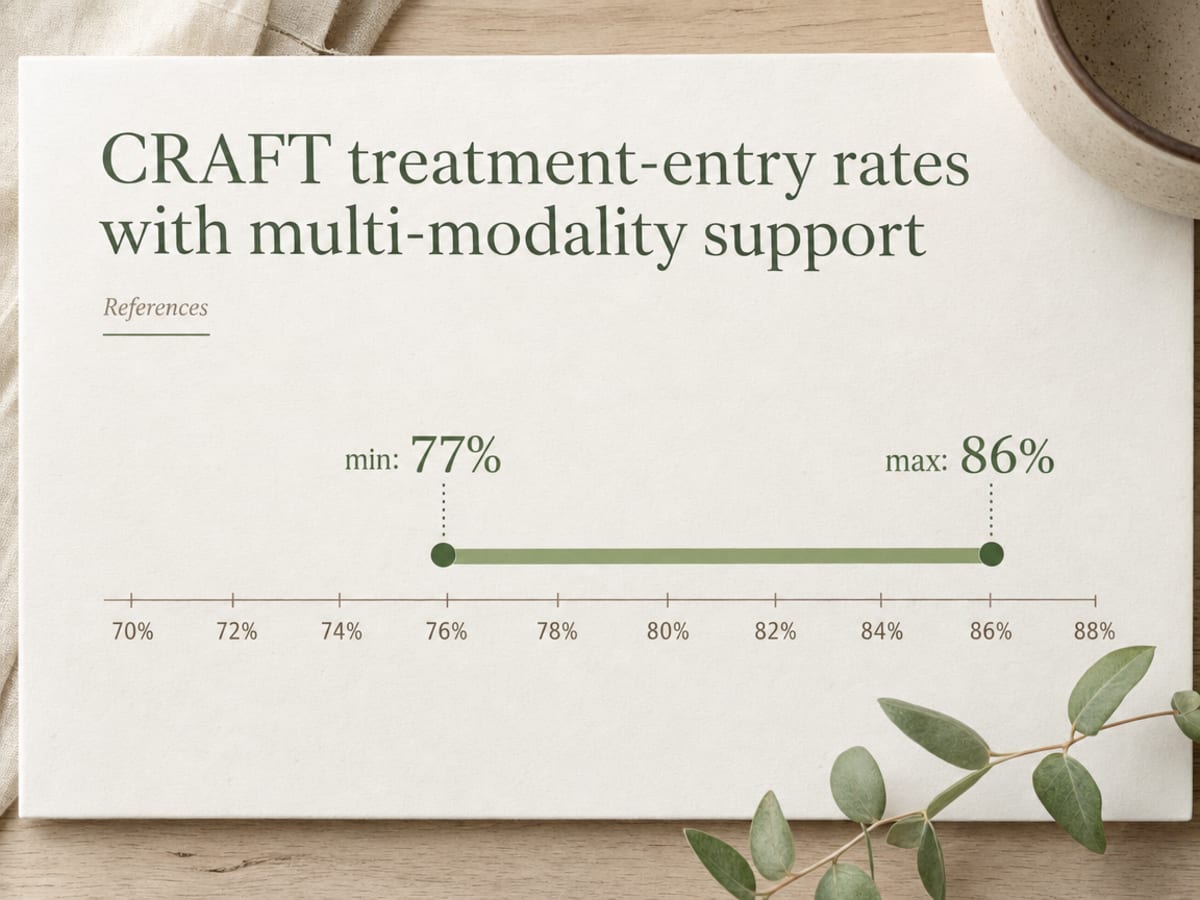
And it works better. A meta-analysis of family-based approaches found that CRAFT produced roughly three times the patient treatment engagement of Al-Anon or Nar-Anon and about twice the engagement of the Johnson Institute intervention, with roughly two-thirds of treatment-resistant individuals eventually entering care when a concerned family member was trained in the approach 9. NIAAA puts it plainly: CRAFT has been shown to be more effective than confronting someone in a classic “intervention” for getting them to accept treatment 6.
The Short List of Things to Stop Doing
You’ve probably already tried a few of these. Most families have. It’s not a character flaw; it’s what love looks like when it’s panicking.
Stop lecturing. If you’ve said it twice, they heard it. The third, fourth, and fifteenth time just teaches them to tune you out when you walk into the room.
Stop lying for them. Calling their boss, covering with the kids, explaining to your mother why they missed Easter again. Every cover story buys them another week of not having to look at what’s happening. SAMHSA’s family guidance leans hard on being direct about what you actually see, not softening it 2.
Stop making ultimatums you won’t keep. “If you drink tonight, I’m leaving” said six times without leaving teaches them your word doesn’t bind. Say less, do more.
Stop staging the hotel-room ambush. The surprise-confrontation model gets worse results than quieter, trained approaches 6.
Stop trying to out-argue the addiction at midnight. Nothing you say to someone who is high or blackout drunk will stick in the morning. Wait for coffee.
And stop blaming yourself for not having fixed this already. You didn’t cause it. You can’t white-knuckle them into recovery. What you can do is change the next conversation, and that starts tomorrow, not tonight.
The Safety Floor: When Talking Isn’t Enough
Opioids and Fentanyl: Keep Naloxone in the House
If your family member uses opioids of any kind, prescription painkillers, heroin, or anything bought on the street, you need naloxone in the house tonight. Not next week. Not after the next conversation. Tonight.
Fentanyl is in almost everything on the illicit market right now, including pills that look exactly like Percocet or Xanax. That means an overdose isn’t a dramatic Hollywood scene. It’s your son slumped on the bathroom floor, breathing wrong, lips going gray.
Naloxone, sold as Narcan, is a nasal spray that reverses an opioid overdose by restoring normal breathing within two to three minutes. The CDC is explicit that it will not harm someone even if the overdose turns out to involve a non-opioid drug, so when in doubt, use it 12. In Oklahoma, free naloxone is available by mail and through state distribution channels, so cost is not a reason to go without 19.
Keep two doses. Keep them somewhere you can reach in the dark. Tell everyone in the house where they are, including teenagers. Then follow the response steps: give the naloxone, call 911, keep them breathing, roll them onto their side, and stay with them until help arrives 14.
Alcohol and Benzos: Why Quitting at Home Can Be Dangerous
If your husband drinks a fifth a day, or your sister has been on daily Xanax for years, and they decide tomorrow morning that they’re going cold turkey in the spare bedroom, that is a medical situation, not a willpower situation. NIAAA warns that heavy-drinking withdrawal can escalate into delirium tremens, including hallucinations and seizures, and that medical evaluation is part of taking symptoms seriously, not an overreaction 17.
So when they finally say the words you’ve been waiting to hear, “okay, I’ll stop,” the next sentence out of your mouth should not be “great, let’s do it right now at home.” It should be “let’s call somebody first.” Medically supervised detox exists exactly for this. A nurse watching vitals through the first seventy-two hours is the difference between a hard week and an ambulance ride.
Who to Call and When: 911, 988, or a Detox Line
When something is actively going wrong, your brain will not want to sort through options. So sort them now, while you’re reading this, so you don’t have to think later.
Call 911 if you suspect an overdose or any medical emergency. Blue lips, not breathing, unresponsive, seizing, bleeding, chest pain. Give naloxone if opioids are possible, roll them onto their side, and stay on the line until paramedics arrive. The Oklahoma State Department of Health states it directly: call 911 immediately if you suspect someone is experiencing an overdose 18.
Call 988 if the danger is a mental health or substance use crisis without an immediate medical emergency. Suicidal talk, a psychotic break, a relapse spiraling into something scary, a family member who is drunk and threatening to drive. In Oklahoma, 988 connects you to trained professionals who can walk you through what’s happening and connect you to local urgent recovery clinics and crisis stabilization units 21.
Call a medical detox line like ours when the situation is urgent but not an emergency. They’ve agreed to go. They want to stop but are scared of withdrawal. You don’t know whether what you’re seeing requires a hospital or a bed tonight. That’s the call where a nurse on the other end can tell you what to do in the next hour.
What Happens After ‘Yes’: Detox, MAT, and Continuing Care
When they finally say yes, even a quiet, maybe-tomorrow yes, your chest unclenches for about ten seconds. Then the next question lands: okay, now what?
For most substances, the first stop is detox. That’s the medically supervised part where the body clears what it’s been running on, usually over three to seven days, with a nurse watching vitals and a doctor managing withdrawal symptoms so the first night doesn’t become the reason they quit quitting. At a facility like ours, that means 24/7 monitoring, medication-assisted protocols to take the edge off the worst symptoms, and a bed in a room with a door, not a hallway cot.
Here’s the part families often don’t hear until later: detox is the on-ramp, not the whole highway. NIDA is direct about this. Safe, effective medications and behavioral therapies exist for substance use disorders, and for opioids, treatment commonly combines medication with counseling over months or years 16. For opioid use disorder specifically, that usually means buprenorphine, methadone, or naltrexone, started during or right after detox and continued in outpatient care 15. Stopping at detox and sending someone home with a handshake is where a lot of relapses happen.
So while they’re in detox, the case manager is already working the next step: residential treatment, intensive outpatient, a sober-living bed, a therapist, a MAT prescriber. In Oklahoma, SoonerCare covers both detox and residential substance-use services for eligible members, which matters when your family is already stretched thin 20. Your job in that handoff is smaller than you think. Show up for the family session if they invite you. Ask what you can and can’t know, because confidentiality rules will limit some of it 5. And breathe.
Take Care of Yourself, Even If They Say No
Here’s the sentence nobody wants to hear when they’re drowning: you need to put your own oxygen mask on first. But it’s true, and skipping it is how good families burn down to ash.
If your loved one isn’t ready, you still are. You are still allowed to go to therapy. You are still allowed to sleep eight hours. You are still allowed to let your sister babysit so you can see a movie without your phone face-up on the armrest. None of that is giving up on them. It’s keeping you standing long enough to be useful when the moment turns.
There are places built exactly for people in your spot. Al-Anon and Nar-Anon are free, meet in church basements and on Zoom all over Oklahoma, and are made up of people who have been exactly where you are. SMART Recovery for Family and Friends runs on a different model if twelve-step language isn’t your fit. Family therapy, with or without your loved one in the room, is a real option NIAAA points families toward 7. SAMHSA says the same thing in plainer words: support groups and family therapy don’t just help the person using, they help the whole family hold together 3.
One honest note. The research on family-member interventions shows mixed short-term results, so don’t expect any one meeting to fix how you feel 11. Go anyway. Go twice. The point isn’t a quick fix. The point is that you stop carrying this in a locked room by yourself.
What Families Cannot Do (and Why That’s Not Your Failure)
Here’s the hardest sentence in this whole guide: you cannot make another adult want to be sober. You can change how you talk. You can keep naloxone in the drawer. You can learn CRAFT skills, go to Al-Anon, call a detox nurse at 2 a.m. You still cannot reach inside their chest and flip the switch.
That’s not because you haven’t tried hard enough. The research on family-focused interventions is honest about this. A systematic review of programs designed to support affected family members found no reliable short-term benefit across every outcome studied 10. CRAFT improves the odds of treatment entry. It does not guarantee recovery, and no family approach does.
So if you’ve been doing this for years and they’re still using, you did not fail. You were handed something no one person was ever supposed to carry alone. Keep showing up anyway. That’s the only part that’s actually yours.
If You Want to Talk It Through, Call Us
If you’ve read this far, you’re already doing the work. Here’s the quiet offer: you can call Renewal Springs even if your loved one isn’t ready yet. You don’t need their permission to ask questions. You don’t need a decision made before you dial.
We’re a medical detox in Oklahoma City with 24/7 medically supervised care, medication-assisted protocols for alcohol, opioids, and benzos, and nurses who can tell you whether what you’re describing sounds like a crisis, a conversation, or a bed tonight. We’ll verify insurance for free. We’ll help you think about what to say next. And if the right next call is 988 or 911 instead of us, we’ll tell you that too.
No pressure. Just a human on the phone who’s done this before.
Talk with someone who truly understands right now
Get direct answers and support for guiding your loved one through this difficult moment.
Frequently Asked Questions
What should I say first to a family member I think has an addiction?
Pick a private, calm moment and lead with what you’ve actually seen, not a label. Something like: “I love you, and I’m worried. I noticed the bottles in the garage and I want to talk.” Then stop and listen. SAMHSA’s starting-the-conversation sequence puts direct concern, listening, and concrete help ahead of any ultimatum 1.
Can I force my loved one into treatment if they refuse to go?
No, not in any lasting way. What you can do is change how you talk and respond over time. Family training approaches like CRAFT have been shown to be more effective than surprise-style confrontational interventions at helping someone eventually accept treatment 6. It improves the odds. It doesn’t flip a switch, and that isn’t your failure.
Is it safe for someone to quit alcohol or opioids at home?
Often, no. Heavy alcohol withdrawal can escalate to seizures and delirium tremens, which NIAAA treats as a medical situation requiring evaluation 17. Opioid withdrawal is rarely fatal on its own, but relapse after is high-risk for overdose, which is why federal guidance pairs detox with medications like buprenorphine, methadone, or naltrexone 15.
When should I call 911, and when should I call 988?
Call 911 for a medical emergency: suspected overdose, not breathing, blue lips, unresponsive, or seizing. Give naloxone if opioids are possible and stay until help arrives 18. Call 988 when the crisis is mental health or substance use without an immediate medical emergency, like suicidal talk or a scary relapse. In Oklahoma, 988 connects you to trained professionals 21.
Where can I get support for myself while my family member is still using?
Al-Anon, Nar-Anon, and SMART Recovery for Family and Friends meet across Oklahoma and online, and family therapy is available whether or not your loved one participates 7. SAMHSA points families to support groups and family therapy as help for the whole household, not just the person using 3. You’re allowed to go even if they won’t.
Can I call Renewal Springs if my loved one isn’t ready for treatment yet?
Yes. You don’t need their permission to ask questions, and you don’t need a decision made before you dial. A nurse can help you think through what you’re seeing, talk about what the next conversation might sound like, verify insurance for free, and tell you honestly if the right next call is 988, 911, or us.
References
- Starting the conversation Guide. https://www.samhsa.gov/sites/default/files/starting-the-conversation-guide.pdf
- Helping a Loved One Dealing with Mental and/or Substance Use Disorders. https://www.samhsa.gov/sites/default/files/samhsa_families_family_support_guide_final508.pdf
- Helping Families Cope with Mental Health and Substance Use. https://www.samhsa.gov/mental-health/children-and-families/coping-resources
- THE IMPORTANCE OF FAMILY THERAPY Advisory 39. https://library.samhsa.gov/sites/default/files/pep20-02-02-016.pdf
- TIP 39 Substance Use Disorder Treatment and Family Therapy. https://library.samhsa.gov/sites/default/files/tip-39-treatment-family-therapy-pep20-02-02-012.pdf
- Frequently Asked Questions: Searching for Alcohol Treatment. https://alcoholtreatment.niaaa.nih.gov/FAQs-searching-alcohol-treatment
- Caretaker Support Services – NIAAA Alcohol Treatment Navigator. https://alcoholtreatment.niaaa.nih.gov/support-through-the-process/caretaker-support-resources
- Community reinforcement and family training and rates of treatment entry: a systematic review. https://pubmed.ncbi.nlm.nih.gov/31770469/
- an effective option to engage treatment-resistant substance-abusing individuals in treatment: a meta-analysis. https://pubmed.ncbi.nlm.nih.gov/20626372/
- Affected other interventions: a systematic review and meta‐analysis across addictions. https://pmc.ncbi.nlm.nih.gov/articles/PMC9543616/
- Psychosocial Interventions to Improve Psychological, Social and Physical Wellbeing in Family Members Affected by an Adult Relative’s Substance Use: A Systematic Search and Review of the Evidence. https://pmc.ncbi.nlm.nih.gov/articles/PMC7918716/
- Lifesaving Naloxone | Stop Overdose. https://www.cdc.gov/stop-overdose/caring/naloxone.html
- Naloxone Toolkit | Overdose Prevention – CDC. https://www.cdc.gov/overdose-prevention/hcp/toolkits/naloxone.html
- Risks and How to Reduce Them | Overdose Prevention – CDC. https://www.cdc.gov/overdose-prevention/manage-treat-pain/reduce-risks.html
- Medications for Opioid Use Disorder. https://nida.nih.gov/sites/default/files/tip-63.pdf
- Treatment. https://nida.nih.gov/research-topics/treatment
- Alcohol Use Disorder and Common Co-occurring Conditions. https://www.niaaa.nih.gov/health-professionals-communities/core-resource-on-alcohol/mental-health-issues-alcohol-use-disorder-and-common-co-occurring-conditions
- Opioids. https://oklahoma.gov/health/health-education/injury-prevention-service/drug-overdose/opioid-overdose.html
- Naloxone – Oklahoma.gov. https://oklahoma.gov/health/health-education/injury-prevention-service/drug-overdose/opioid-overdose/naloxone.html
- Mental Health and Substance Abuse Services. https://oklahoma.gov/ohca/individuals/programs/mental-health-and-substance-abuse-services.html
- Comprehensive Crisis Response. https://oklahoma.gov/odmhsas/treatment/comprehensive-crisis-response.html
- ODMHSAS Facilities. https://oklahoma.gov/odmhsas/about/odmhsas-facilities.html


