
Key Takeaways
- A legitimate Oklahoma City medical detox completes a written medical service plan within three hours of admission and keeps a licensed physician reachable 24/7 by phone 1.
- Match the substance to the right care: alcohol and benzodiazepine withdrawal require medical supervision to prevent seizures, and opioid detox should include buprenorphine, methadone, or naltrexone rather than detox alone 4, 10.
- Know which number fits your situation: 911 for medical emergencies, 988 for crisis and transportation help to Oklahoma crisis-stabilization resources, and an admissions line when physically dependent but stable 2.
- Before choosing a facility, compare physician availability, which withdrawal medications they can start on site, SoonerCare or insurance coverage, and whether discharge includes naloxone and a named follow-up prescriber 3, 5.
Before You Call: What a Safe Oklahoma City Detox Actually Does in the First Hour
If you are reading this on a phone, probably in a bathroom or a parked car, you already know something has to change today. That takes courage most people never find. Before you dial, here is what a real medical detox in Oklahoma City will actually do once you walk through the door, so the unknown feels a little smaller.
The front desk will not interrogate you. An intake nurse will take your vitals, ask what you have been using and when you last used, and start a medical history. If you are shaking, nauseous, or scared, say so plainly. That information guides the medications they can offer.
Oklahoma rules give you a concrete benchmark for what should happen next. Medically supervised withdrawal-management facilities in this state are required to complete a medical service plan addressing your stabilization and service needs within three hours of admission, and a licensed physician must be available at least by telephone 24 hours a day, seven days a week 1. In practice, that means within your first few hours you should see:
- Arrival and intake — vitals, a brief history, insurance or self-pay conversation, and belongings secured.
- Medical evaluation — a nurse assesses withdrawal severity; the physician is consulted on your plan.
- Medical service plan completed within three hours — written, specific to you, and explained in plain language.
- First medication dose considered — if clinically appropriate, something to blunt the worst symptoms before they peak.
If a facility cannot describe this timeline when you call, that is a signal to keep dialing. You deserve a program where a physician is reachable at any hour and a plan exists before the first hard night. Making the call is the hardest part. The structure on the other end is already built for you 1.

How to Tell if a Facility Is Actually a Medical Detox
The Five Screening Questions to Ask on the Phone
A real medical detox will not flinch at direct questions. If the person who answers sounds more like a salesperson than a nurse, hang up and try the next number. You are allowed to interview them.
Keep these five questions on your screen when you call:
- Is a licensed physician available 24/7, at least by phone? Oklahoma rule requires it for medically supervised withdrawal management, so the answer should be an easy yes 1.
- How soon after I arrive will I have a written medical service plan? You want to hear “within three hours,” because that is the state standard for stabilization and service planning 1.
- What withdrawal symptoms can you medicate on site, and what medications do you use? For opioids, ask specifically whether they can start buprenorphine, methadone, or naltrexone, since detox without medication is not recommended for opioid use disorder 4, 8.
- Can you handle my situation safely? Name what you have been using, how much, and when you last used. Mention alcohol, benzodiazepines, or any mix. The nurse should respond with clinical questions, not reassurances.
- What happens on discharge day? A real program plans your next step before you walk in, including naloxone and a warm handoff when appropriate 5.
If any answer is vague, write it down and call somewhere else. You are not being difficult. You are protecting yourself.
Oklahoma Rules That Separate Real Medical Detox From Marketing
Plenty of websites use the word “detox.” Fewer facilities meet the standard the state actually sets. Knowing the rule helps you tell the difference in about two minutes on the phone.
Oklahoma’s Department of Mental Health and Substance Abuse Services, under Chapter 18, holds medically supervised withdrawal-management facilities to specific clinical requirements. Two of them matter most to you tonight:
- A medical service plan within three hours of admission that addresses medical stabilization and your service needs, written and specific to you 1.
- A licensed physician available 24 hours a day, seven days a week, at least by telephone, so a doctor can authorize medication and respond to complications overnight 1.
You can also cross-check nearby options independently using SAMHSA’s FindTreatment.gov locator, which searches by state, county, and distance 14. Use it as a second opinion, not as your only call. Then pick up the phone.
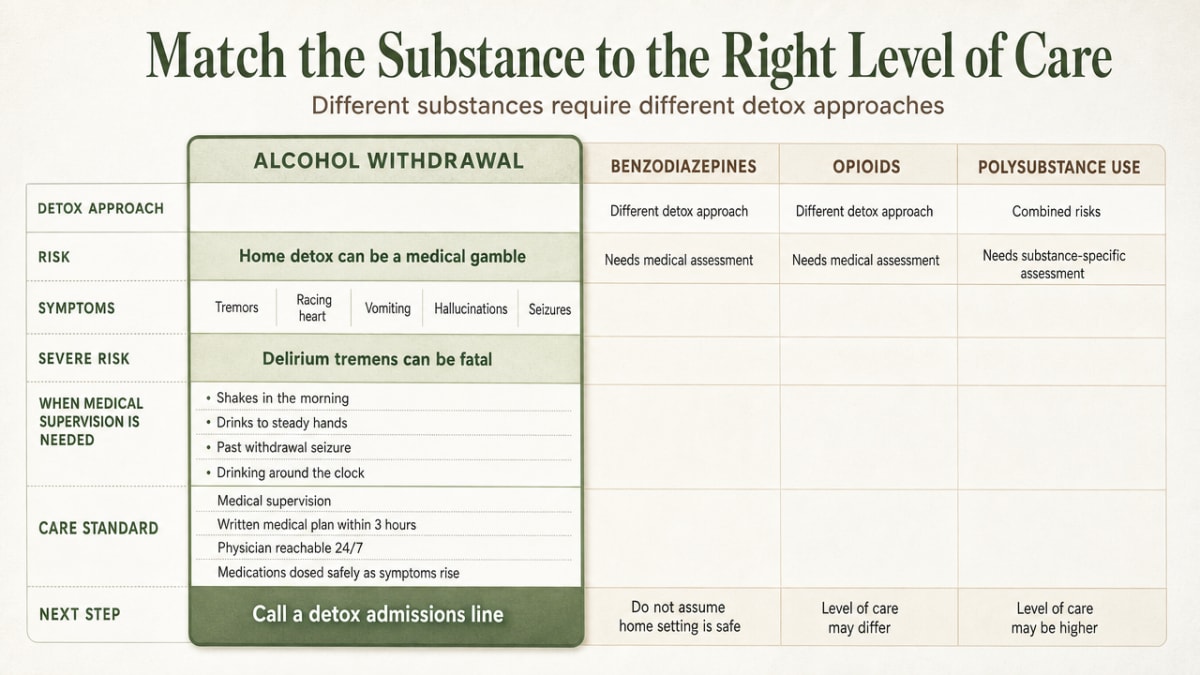
Match the Substance to the Right Level of Care
Alcohol Withdrawal: Why Home Detox Can Kill You
If you have been drinking heavily every day for weeks or longer, stopping cold at home is not a show of willpower. It is a medical gamble. Alcohol withdrawal can cause tremors, racing heart, vomiting, hallucinations, and seizures. In its severe form, delirium tremens, it can kill you.
You do not need to score your own symptoms to know whether you qualify for a medical setting. If you shake in the morning, drink to steady your hands, have ever had a withdrawal seizure, or have been drinking around the clock, you need medical supervision. Oklahoma’s withdrawal-management standard exists precisely for this: a written medical plan within three hours of admission and a physician reachable 24/7, so medications like benzodiazepines can be dosed safely as symptoms rise 1.
Call a detox admissions line before your next drink wears off. Tell them how much you drink, how often, and when you last stopped. That one honest sentence lets a nurse plan your first dose before you walk through the door.
Benzodiazepines: Never Stop Cold, Ask About a Taper
Xanax, Klonopin, Ativan, Valium. If you have been taking any of these daily for more than a few weeks, your body has adapted to them. Stopping suddenly is dangerous in a way that surprises most people, including some prescribers.
FDA-approved benzodiazepine labeling warns that abruptly discontinuing these medications can cause serious reactions, including seizures, severe mental and nervous-system changes, and suicidal thoughts, and it recommends a patient-specific gradual taper 10. The FDA has flagged benzodiazepine tapering as a clinical priority and points to the 2025 Joint Clinical Practice Guideline on Benzodiazepine Tapering as the framework clinicians should follow 9. In plain language: do not quit on your own, and do not let anyone rush you.
When you call a facility, ask directly: “Can you manage a benzodiazepine taper on site, or will you transfer me to a higher level of care?” A real medical detox will answer with specifics. They will want to know which benzo you take, your daily dose, how long you have been on it, and whether you also drink or use opioids. If a program hedges, hang up. Your taper schedule should be built around you, not around a facility’s convenience.
You are not weak for being physically dependent on a medication a doctor prescribed. You are human. The next step is a phone call, not willpower.
Opioids and Fentanyl: Detox Alone Is Not the Finish Line
Opioid withdrawal rarely kills you directly. What kills people is what happens after. Your tolerance drops in a matter of days, and if you use the same amount you used before detox, your body cannot handle it. That is how overdose deaths cluster in the first weeks after someone leaves a detox bed.
The CDC is explicit on this: detox on its own, without medication for opioid use disorder, is not recommended, because the risks of resumed use, overdose, and overdose death go up 4. The question to ask on the phone is not “Can you get me through withdrawal?” It is “What medication can you start before I leave, and who will prescribe it next week?”
There are three FDA-approved medications for opioid use disorder, and SAMHSA’s TIP 63 reviews each one along with the counseling and monitoring that go with it 8. In plain terms:
- Buprenorphine — a partial opioid that eases withdrawal and cravings; usually started once you are in early withdrawal and continued as an outpatient.
- Methadone — a full opioid dispensed daily through a licensed opioid-treatment program; often used when buprenorphine has not worked or fentanyl exposure is heavy.
- Naltrexone — a monthly injection that blocks opioids; started only after you are fully off opioids, usually a week or more past last use.
Ask which of these a facility can start on site, and ask who will continue the prescription after discharge. If the answer is “we only do detox,” keep looking or confirm they have a warm handoff lined up 5. You deserve both the first week and the second month covered.
Polysubstance Use: One Honest Conversation, Not Two Programs
Most people who need detox are not using just one thing. Alcohol with Xanax. Fentanyl with meth. Prescribed opioids with a nightly drink to sleep. If that describes you, you are not an edge case. You are the norm.
The mistake is downplaying one substance to seem like a simpler admission. Do not do that. The nurse on the intake call needs the full picture, because benzos and alcohol together change the medications they can safely give, and stimulants on board change what withdrawal will look like in the first 24 hours. Oklahoma’s medical service plan rule exists so your plan accounts for everything you are coming off of, not just the headline substance 1.
Tell them everything. Doses, times, last use. Nothing you say will shock them, and nothing you say will be used to turn you away. It will be used to keep you alive through the first night.
911, 988, or Admissions Line: Who to Call Right Now
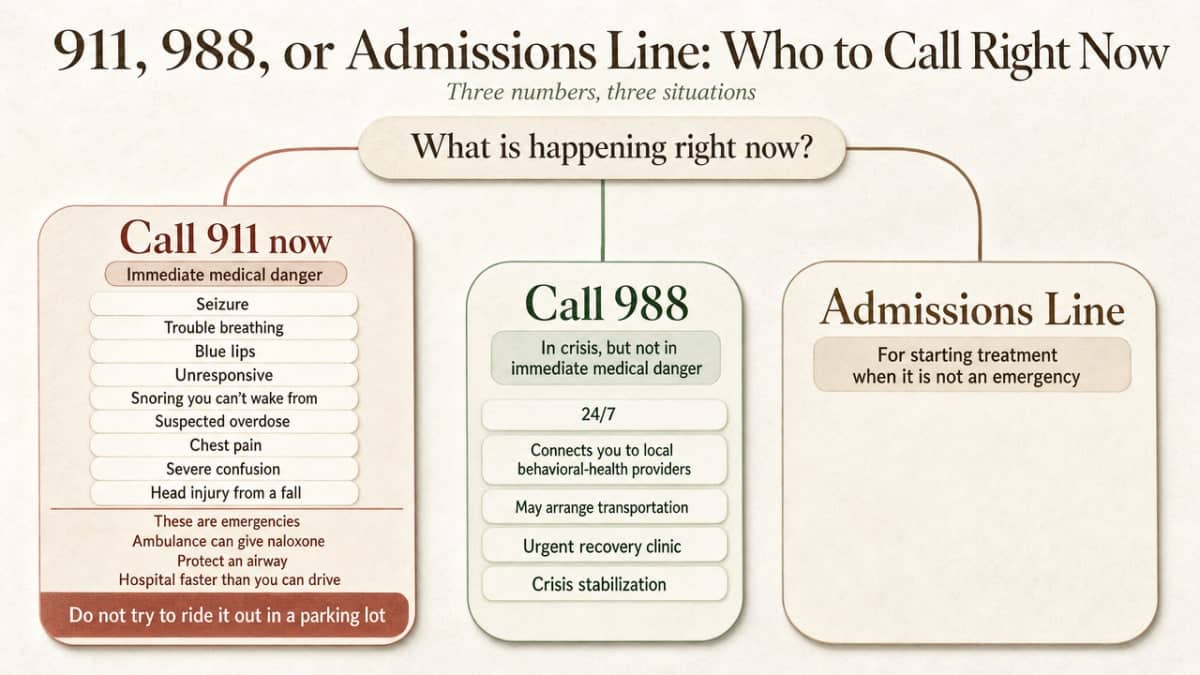
Three numbers, three different situations. Getting this right matters more than almost anything else on this page, because the wrong call can waste minutes you do not have.
Call 988 if you are in crisis but not in immediate medical danger. Oklahoma’s 988 line operates 24 hours a day, seven days a week, can connect you to local behavioral-health providers, and may arrange transportation to an urgent recovery clinic or crisis-stabilization unit when a higher level of care is needed 2. Use 988 when you are overwhelmed, suicidal, or do not know what kind of help you need next. The person on the other end will stay with you while you figure it out. 988 is not a replacement for 911 when a life is in immediate danger.
Call a detox admissions line when you are physically dependent but medically stable right now: shaking, sweating, nauseous, cramping, craving, last use within the past several hours, or scared about what happens when the next dose wears off. Admissions nurses can start a plan over the phone, confirm a bed, and tell you when to come in.
If you are not sure which number fits, start with 988 and let a trained counselor help you sort it 2. You will not be judged for calling the “wrong” one. You will be helped toward the right one.
Paying For Detox in Oklahoma Without Guessing
Insurance, SoonerCare, and Free Benefits Verification
Money fear keeps people in parking lots long after they have decided to call. Push past that. A good admissions team will verify your benefits for free, usually in the time it takes to boil water, and tell you in plain numbers what your insurance will cover before you commit to anything.
Have your insurance card ready, or just the member ID and the phone number on the back. If you cannot find the card, admissions can often look you up with a date of birth and the carrier’s name. Ask three things on the call:
- What will my plan pay for medical detox at your facility? Get a dollar range or a percentage, not a shrug.
- Do I need prior authorization before I can be admitted? Many plans do; a competent admissions team handles the paperwork while you drive in.
- Will my plan continue to cover medication after I discharge? This matters most for buprenorphine, methadone, or naltrexone follow-up.
If you have SoonerCare, Oklahoma Medicaid covers medically necessary medication treatment for opioid use disorder through enrolled opioid-treatment programs, including methadone, subject to eligibility and authorization requirements 3. Ask the admissions nurse to confirm that your detox facility either accepts SoonerCare directly or can refer you to a SoonerCare-enrolled MAT provider for your next step 3.
What to Say if You Have No Insurance and No Cash
Say it exactly like this: “I don’t have insurance and I can’t pay out of pocket. What are my options?” Then stop talking and let them work.
A real admissions team hears that sentence every day. They can screen you for SoonerCare eligibility on the spot, point you toward state-funded withdrawal-management beds, or connect you with Oklahoma’s crisis-response pathway. Oklahoma’s 988 line operates 24/7 and can route you to local behavioral-health providers and, when needed, arrange transportation to an urgent recovery clinic or crisis-stabilization unit 2.
If a facility turns you away for cost without offering a next step, call 988 or search SAMHSA’s FindTreatment.gov by county and distance for another nearby option 14, 2. You still have a path. It just takes one more call.
Pathways: Veterans, Women, and Men
Veterans and VA-Coordinated Detox in OKC
If you served, your care should be coordinated, not duplicated. The VA explicitly includes medically managed detoxification as part of its substance-use treatment, alongside buprenorphine, injectable naltrexone, and methadone for opioid dependence, plus counseling, residential care, and relapse-prevention services 11, 12. That matters when you call an Oklahoma City detox facility: you want to know whether they will coordinate with VA for your medication continuation and follow-up, or whether you should go directly through VA.
Ask the admissions nurse two questions. First: “Have you worked with VA patients before, and can you share records with my VA provider?” Second: “If I start buprenorphine or methadone here, who writes the next prescription?” If the facility cannot answer cleanly, call the Oklahoma City VA directly and ask for the substance-use clinic. Either path gets you to the same medications 11. The point is that one call tonight starts the handoff.
Women-Specific and Men-Specific Programs
Who you detox around matters. For some women, a mixed-gender unit raises the odds you walk out early, especially if trauma is part of the story. For some men, a program built around men lowers the pressure to perform calm you do not feel. Neither preference is weakness.
When you call, ask plainly: “Do you offer gender-specific sleeping areas, groups, or programming?” Then ask what that looks like in practice during the first 72 hours, when you will be most uncomfortable. If you are pregnant, say so on the first call so the nurse can plan around medications that are safe in pregnancy. If you have childcare constraints, say that too; a good admissions team will help you problem-solve before admission, not after.
Getting There: Transportation, What to Bring, What to Leave
You have made the decision. Now the logistics. Keep this simple, because your brain is already working hard.
Getting there. If a sober friend or family member can drive you, that is the easiest route. If not, ask the admissions nurse whether the facility offers pickup or can coordinate a ride; many do, especially for same-day admissions. If you are relying on public transit, EMBARK operates Oklahoma City’s buses, RAPID transit, streetcars, and paratransit services, and the admissions team can usually tell you the closest stop to their address 13. If you cannot afford a ride and no one can get you there, call 988. Oklahoma’s crisis line can connect you with local behavioral-health providers and, when a higher level of care is needed, may arrange transportation to an urgent recovery clinic or crisis-stabilization unit 2. Do not let a missing ride be the thing that stops you.
What to bring.
- Photo ID and insurance card, or just the member ID.
- A written list of every medication you take, including doses and the last time you took each one.
- Comfortable clothes for three to seven days, pajamas, slip-on shoes.
- Phone and charger, a short list of contact numbers written on paper in case your phone is secured.
- Glasses, CPAP, or any medical device you depend on.
What to leave. Alcohol, drugs, drug paraphernalia, weapons, mouthwash with alcohol, aerosols, and anything valuable or sentimental that you would hate to misplace. Most facilities also hold cash, jewelry, and prescription bottles at intake and return them at discharge.
If something is missing when you arrive, the staff will work around it. Showing up matters more than packing perfectly.
After Detox: Discharge Planning Starts on Day One
Here is the part most people do not know: a good detox is already planning your discharge before you finish your first meal there. That is not the staff rushing you out. That is them keeping you alive through the second week, which is statistically the dangerous one if opioids are part of your story.
Ask your care team on day one what medication you will leave with and who will prescribe it next. For opioid use disorder, CDC guidance is clear that higher-risk patients should be trained to respond to overdose and given naloxone before discharge, and that medication induction should begin immediately when clinically appropriate rather than waiting for a referral weeks out 5. You want a warm handoff, meaning a named clinician, a scheduled appointment, and a prescription that does not lapse between buildings.
Ask the same question about counseling, housing, and work. SAMHSA’s TIP 63 underscores that medications for opioid use disorder work best alongside counseling and the recovery supports around them, not instead of them 8. If you have SoonerCare, confirm your next MAT provider is enrolled so your methadone or buprenorphine does not stop at the door 3.
Leaving with a plan is leaving with a chance. Make them write it down.
You Are Not the Only One in Oklahoma Making This Call
Whatever shame you are carrying right now, set it down for a minute. You are not the first person in Oklahoma to sit in a car at midnight trying to decide if tonight is the night. In FY25 alone, 9,397 Oklahomans received opioid-treatment and support services, including medication-assisted treatment, through state-reported programs 7. That is tens of thousands of first phone calls, tens of thousands of first mornings in a detox bed, tens of thousands of people who were exactly where you are and picked up anyway.
The need is real. Oklahoma recorded 1,015 provisional overdose deaths in 2024 6. Those are neighbors, coworkers, siblings. The point is not to scare you. The point is that the help on the other end of the phone is built for the size of this problem, and a seat at the table is yours.
Pick up the phone. One call tonight is enough.
Get Immediate Help With Your Detox Questions
Speak with a medical professional in Oklahoma City now for support or fast admission guidance.
Frequently Asked Questions
Can I get into a medical detox in Oklahoma City today?
Often, yes. Call an admissions line directly and say you need same-day admission. In Oklahoma, medically supervised withdrawal-management facilities must complete a written medical service plan within three hours of your arrival and keep a physician reachable 24/7 1. If one facility is full, ask them to refer you, or search SAMHSA’s FindTreatment.gov by county and distance for another nearby option 14.
What is the difference between calling 911, 988, and a detox admissions line?
Call 911 for medical emergencies: seizure, trouble breathing, suspected overdose, severe confusion, or unresponsiveness. Call 988 when you are in crisis but not in immediate medical danger; Oklahoma’s 988 line operates 24/7, connects you to local behavioral-health providers, and may arrange transportation to an urgent recovery clinic or crisis-stabilization unit 2. Call a detox admissions line when you are physically dependent but stable and ready to come in.
Is it safe to detox from alcohol or benzodiazepines at home?
No. Both can cause seizures and, in alcohol’s case, delirium tremens that can be fatal. FDA labeling warns that abruptly stopping benzodiazepines can cause seizures, severe nervous-system reactions, and suicidal thoughts, and recommends a patient-specific gradual taper 10, 9. Oklahoma’s withdrawal-management rule exists so a physician can authorize medications as symptoms rise 1. Call a medical detox before your next drink or dose wears off.
Will SoonerCare or my insurance cover medical detox in Oklahoma?
SoonerCare covers medically necessary medication treatment for opioid use disorder through enrolled opioid-treatment programs, including methadone, subject to eligibility and authorization 3. Private plans vary. Ask admissions to run a free benefits check and tell you what your plan will pay, whether prior authorization is required, and whether medication coverage continues after discharge. If you have no insurance, say so plainly and ask about state-funded options.
What medications can a detox facility start for opioid withdrawal?
SAMHSA’s TIP 63 reviews the three FDA-approved medications for opioid use disorder: buprenorphine, methadone, and naltrexone, each paired with counseling and recovery supports 8. CDC guidance is clear that detox without medication is not recommended for OUD because risk of overdose rises after tolerance drops 4. Ask which medication the facility can start on site and who will prescribe it after discharge, with naloxone sent home with you 5.
What should I bring to admission, and what happens if I have no ride?
Bring a photo ID, insurance card or member ID, a written list of current medications and doses, three to seven days of comfortable clothes, phone and charger, and any medical device you depend on. Leave alcohol, drugs, weapons, and valuables at home. If you have no ride, ask about facility pickup, use EMBARK buses or paratransit 13, or call 988 for transportation help 2.
References
- CHAPTER 18. STANDARDS AND CRITERIA FOR …. https://oklahoma.gov/content/dam/ok/en/odmhsas/documents/policy/provider-certification/administrative-rules/2025/PC–Chapter-18_9-1-25.pdf
- Comprehensive Crisis Response. https://oklahoma.gov/odmhsas/treatment/comprehensive-crisis-response.html
- 317:30-5-241.7. Medication-assisted treatment (MAT) services …. https://oklahoma.gov/ohca/policies-and-rules/xpolicy/medical-providers-fee-for-service/individual-providers-and-specialties/outpatient-behavioral-health-services/medication-assisted-treatment-services-for-eligible-individuals-with-opioid-use-disorder.html
- Opioid Use Disorder: Treating. https://www.cdc.gov/overdose-prevention/hcp/clinical-care/opioid-use-disorder-treating.html
- Linking People with Opioid Use Disorder to Medication Treatment. https://www.cdc.gov/overdose-prevention/hcp/clinical-guidance/linkage-to-care.html
- Provisional Drug Overdose Death Counts. https://www.cdc.gov/nchs/nvss/vsrr/drug-overdose-data.htm
- FY26-27 Mental Health Block Grant Report. https://aem-prod.oklahoma.gov/content/dam/ok/en/odmhsas/documents/about/public-information/grants-and-solicitations/FY26-27-Mental-Health-Block-Grant-Report.pdf
- TIP 63: Medications for Opioid Use Disorder. https://library.samhsa.gov/product/tip-63-medications-opioid-use-disorder/pep21-02-01-002
- Supporting Clinical Practice Guidelines for Drugs with Abuse Potential. https://www.fda.gov/drugs/food-and-drug-administration-overdose-prevention-framework/supporting-clinical-practice-guidelines-drugs-abuse-potential
- label – accessdata.fda.gov. https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/211635s010lbl.pdf
- Health Care Providers Treating SUD – Mental Health. https://www.mentalhealth.va.gov/healthcare-providers/sud.asp
- Substance Use Treatment For Veterans – VA.gov. https://www.va.gov/health-care/health-needs-conditions/substance-use-problems/
- Guide to City Government. https://www.okc.gov/Government/About-OKC/Guide-to-City-Government
- FindTreatment.gov (English). https://www.samhsa.gov/resource/dbhis/findtreatmentgov-english


