
Key Takeaways
- Quitting opioids alone in Oklahoma City has grown far more dangerous as fentanyl drove 86% of the state’s opioid overdose deaths in 2024 1, making medically supervised detox a safety issue rather than a willpower one.
- Supervised detox uses buprenorphine, methadone, or naltrexone alongside 24/7 monitoring to stabilize withdrawal, with medication choice depending on use history, fentanyl exposure, and where a person is in the withdrawal timeline 4.
- Cost is rarely the true barrier locally: SoonerCare covers detox and residential SUD services with prior authorization handled by the facility, and private insurance typically covers medically necessary detox 11.
- Before choosing an Oklahoma City program, compare 24/7 medical staffing, access to all three FDA-approved medications, polysubstance intake screening, and a written aftercare bridge to ongoing MAT, since detox alone is not treatment 6.
Why Your Body Fights Back When You Try to Quit Opioids Alone
If you’ve tried to stop using opioids on your own and the withdrawal drove you back within a day or two, understand that this is a physiological response, not a lack of willpower. Your nervous system, adapted to opioid presence, reacts intensely when these substances are abruptly removed. This leads to severe symptoms like bone pain, vomiting, sweats, restless legs, and intense anxiety. This “cold turkey” method is not only painful but, in the current fentanyl era, significantly riskier than it once was.
The landscape of opioid use has changed dramatically. Fentanyl was involved in 86% of opioid-related overdose deaths in Oklahoma in 2024 1. This statistic highlights that the drugs available today are more potent and unpredictable. Attempting to detox alone and then relapsing at a previous dose can be fatal due to decreased tolerance and the high potency of fentanyl. Medication-assisted detox addresses withdrawal as a medical event, offering a safer and more manageable path.
What Medication-Assisted Detox Actually Does
Medication-assisted detox utilizes FDA-approved medications to stabilize your brain and body as opioids exit your system. Regular opioid use causes your brain to reduce its natural pain-relieving chemicals. When opioids are suddenly stopped, this creates a neurological gap, resulting in severe withdrawal symptoms like muscle pain, sweating, and extreme restlessness.
Medications such as buprenorphine and methadone bridge this gap by attaching to the same brain receptors as opioids. However, they do so without producing the same euphoric high and provide a steady effect, reducing the intensity of withdrawal symptoms. This allows for a calmer heart rate, improved sleep, and overall stabilization. Naltrexone, another medication, functions differently; it is used post-withdrawal to block opioid effects if a person uses again 4.
Beyond medication, supervised detox includes essential safety measures: nurses monitoring vital signs, hydration, and support for nausea and anxiety. The Substance Abuse and Mental Health Services Administration (SAMHSA) emphasizes that these medications, combined with counseling, are effective in reducing opioid use, preventing overdose deaths, and improving recovery outcomes 8. This approach significantly lessens the severity of withdrawal, making sustained recovery more achievable.
The Three Medications: Buprenorphine, Methadone, Naltrexone
Buprenorphine: The Most Common Starting Point
Buprenorphine is frequently the initial medication for opioid detox. As a partial opioid agonist, it partially activates the same brain receptors as more potent opioids like fentanyl or heroin. This partial activation is crucial because it alleviates severe withdrawal symptoms such as muscle pain, sweating, and anxiety, without inducing the intense high associated with full opioids 4.
Buprenorphine also has a “ceiling effect,” meaning that increasing the dose beyond a certain point does not increase its effects, contributing to its safety profile in a supervised setting. Precise timing for the first dose is critical; administering buprenorphine too early, while other opioids are still highly active, can trigger severe precipitated withdrawal. Medical staff use scoring tools to determine the optimal moment for the first dose, ensuring patient safety 13.
Methadone: When a Full Agonist Is the Right Call
Methadone is a full opioid agonist that fully activates opioid receptors, providing a steady level of medication that prevents the highs and crashes associated with illicit opioid use. It is often recommended for individuals with extensive histories of opioid use, high daily fentanyl intake, or those who have not found success with buprenorphine 4.
In the United States, methadone for opioid use disorder is administered through federally regulated opioid treatment programs 9. This involves a structured approach including initial daily dosing, counseling, monitoring, and a gradual increase in take-home privileges as stability is achieved. If methadone is recommended over buprenorphine, it reflects a clinical assessment of the patient’s specific needs to effectively manage withdrawal.
Naltrexone: After Withdrawal, Not During It
Naltrexone is an opioid antagonist, meaning it blocks opioid receptors. It prevents opioids from attaching to these receptors, thereby eliminating their euphoric effects if used 4.
Crucially, naltrexone can only be started after a person has fully completed opioid withdrawal. Administering it while opioids are still active in the system can induce severe, immediate withdrawal. Therefore, naltrexone is typically introduced later in the recovery process, often as a monthly extended-release injection, once the body is clear of opioids 7. This medication offers a protective measure for individuals who prefer not to be on a daily opioid-based medication, helping to maintain abstinence after detox.
The First 72 Hours: What Supervised Detox Actually Feels Like
Understanding the process of supervised detox can alleviate anxiety. Here’s a breakdown of what to expect during the initial 72 hours:
Hours 0–12: Intake, assessment, and waiting for the right moment
Upon arrival, the initial hours involve a calm intake process. Medical staff will take your vitals, and a clinician will gather information about your substance use history, including the type, amount, and last use of opioids, as well as any other substances, past detox attempts, and mental health history. This information is critical for your safety and is not a judgment.
A physical exam and lab work are also conducted. The timing of buprenorphine administration is crucial to avoid precipitated withdrawal. Staff use the Clinical Opiate Withdrawal Scale (COWS) to ensure buprenorphine is given only when your COWS score reaches 11 or higher, indicating your body is ready to safely receive it 13. For individuals coming off methadone, a longer tapering process is involved 13.
Hours 12–48: Induction and the turn
Once cleared, the first dose of buprenorphine is administered. Most individuals experience significant relief within an hour, with muscle pain, sweating, and restlessness subsiding enough to allow for rest. This marks a turning point, providing a foundation for stabilization.
Nurses continuously monitor vital signs. Medications are available to manage symptoms like nausea and sleeplessness. Additional buprenorphine doses are adjusted based on your symptom response 4, allowing most people to finally achieve restful sleep.
Hours 48–72: Stabilizing and looking ahead
By the third day, your medication dose is typically stable, and the most severe acute withdrawal symptoms have passed. You will likely be able to eat and feel more stable. At this stage, discussions shift towards post-detox planning, as detox alone is not a complete treatment for opioid use disorder 6. The team will help arrange your transition to ongoing Medication-Assisted Treatment (MAT), counseling, or residential care.
While three days of detox does not resolve all issues, it provides a critical window of stability, making the next steps in your recovery journey possible.
Why Fentanyl Changed the Detox Conversation in Oklahoma
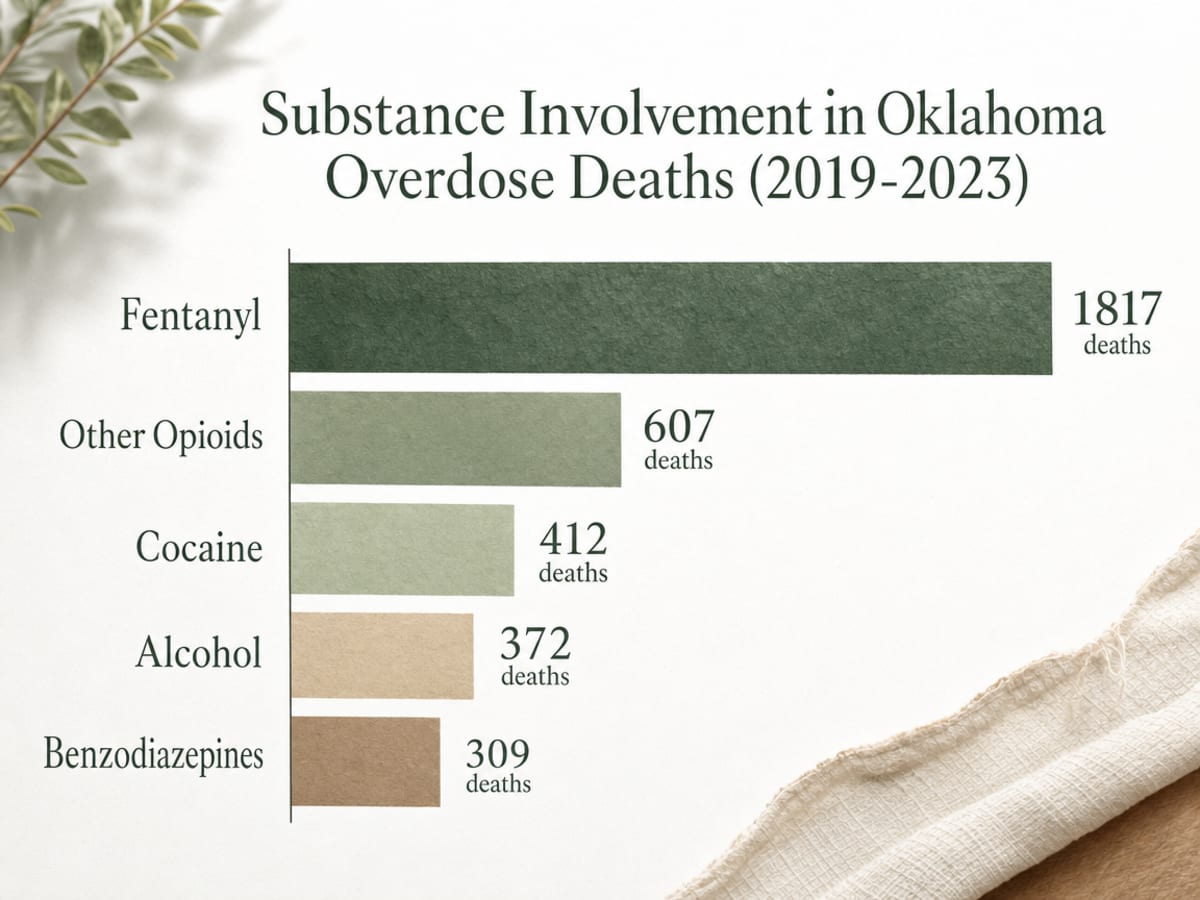
The opioid supply has drastically changed over the past decade, with fentanyl now a dominant and dangerous factor. Fentanyl is significantly more potent and fast-acting, and it is frequently mixed into various illicit drugs. This shift is clearly reflected in Oklahoma’s overdose statistics.
Between 2019 and 2023, Oklahoma recorded 1,817 overdose deaths involving fentanyl, far exceeding other substances like other opioids (607), cocaine (412), alcohol (372), and benzodiazepines (309) 2. Many of these deaths involved polysubstance use, meaning multiple substances were present.
Polysubstance use complicates detox significantly. If opioids are used alongside benzodiazepines, alcohol, or stimulants, withdrawal symptoms will not be limited to typical opioid withdrawal. Benzodiazepine withdrawal can cause seizures, and alcohol withdrawal can be life-threatening. A detox program must account for all substances involved, which is why comprehensive intake assessments are crucial. Attempting cold turkey detox at home is particularly dangerous now, as the current fentanyl supply is unforgiving of any loss of tolerance, increasing the risk of fatal overdose upon relapse.
The detox plan you need today must be tailored to the specific substances currently in your system, acknowledging the unique challenges posed by fentanyl.
The Three Questions You’re Not Asking Out Loud
“Will I Be Judged?”
It’s common to fear judgment when seeking help for opioid use. Many individuals have experienced stigmatization in healthcare settings. However, a medically supervised detox operates as a clinical environment focused on patient safety, not judgment. The intake questions about your substance use history are essential for tailoring a safe and effective treatment plan, as incorrect medication timing can worsen withdrawal 13. Your honest answers are crucial for your well-being.
“Am I Just Trading One Drug for Another?”
This concern is a common misconception. While buprenorphine and methadone interact with the same brain receptors as illicit opioids, their action is fundamentally different. They provide steady, controlled levels of medication without inducing a euphoric high, and their doses are clinically managed, not driven by cravings or tolerance. SAMHSA confirms that these medications are effective in reducing opioid use, preventing overdose deaths, and improving recovery outcomes when combined with counseling 8. This constitutes treatment, not a replacement addiction. Just as insulin treats diabetes, buprenorphine helps the brain adapt back to a stable state after opioid dependence.
“Can I Actually Afford This?”
Financial concerns are a significant barrier. In Oklahoma, if you have SoonerCare (Medicaid), detox and residential substance use disorder services are covered benefits for eligible individuals, though prior authorization is required 11. This coverage includes medication, room and board, monitoring, and transition planning. For those with private insurance, medically supervised detox is typically covered as a medical necessity. Facilities can verify your benefits and provide information on out-of-pocket costs, often within the same day. It’s important to inquire directly about costs rather than assuming it’s unaffordable.
SoonerCare, Insurance, and Paying for Detox in Oklahoma
Financial barriers often prevent individuals from seeking necessary care. In Oklahoma, SoonerCare, the state’s Medicaid program, covers detox and residential substance use disorder services for eligible children and adults, requiring prior authorization 11. Outpatient services are also covered. Importantly, the detox facility typically handles the prior authorization paperwork on your behalf during the assessment phase, so you won’t be burdened with it during withdrawal.
For individuals with private insurance, medically supervised detox is almost universally covered as a medical necessity. The specifics, such as deductibles, network providers, and approved duration of stay, vary by plan. Facilities can conduct a benefits check by phone, providing clarity on your financial obligations before you commit to treatment.
Even without insurance coverage, it is crucial to reach out for help. Oklahoma’s public system, coordinated through ODMHSAS, assists individuals who cannot self-pay. Do not let uncertainty about costs deter you from seeking life-saving treatment.
Why Detox Alone Isn’t Treatment — and What Has to Come Next
It’s vital to understand that managing acute withdrawal is not the same as treating opioid use disorder. The American Society of Addiction Medicine (ASAM) explicitly states that opioid withdrawal management without ongoing care is not a sufficient treatment method and is not recommended 6.
Effective recovery requires a “bridge” to ongoing care. For most, this means continuing buprenorphine or methadone post-detox. SAMHSA’s 2024 guidance emphasizes that medications for opioid use disorder reduce opioid use, overdose deaths, and recidivism, advocating for comprehensive treatment models over detox-only approaches 8. Comprehensive care typically includes outpatient counseling, medication management by a prescriber, and potentially residential care or intensive outpatient programs if a safe home environment is not available. A quality detox program will facilitate this transition before discharge.
What to Look For in an Oklahoma City Detox Program
When choosing a detox program, especially in the context of fentanyl’s prevalence, certain features are non-negotiable:
- Round-the-clock medical staffing: Withdrawal symptoms can emerge at any time. A safe program must have licensed nurses and medical oversight available 24/7.
- Access to all three FDA-approved medications: Inquire if buprenorphine, methadone access, and naltrexone are all part of the clinical options. A program that only offers one medication may not be equipped to provide individualized care 4.
- A written aftercare plan before discharge: ASAM stresses that detox without ongoing opioid use disorder treatment is not recommended 6. A reputable program will ensure your next appointment and medication continuation are scheduled before you leave.
- Upfront insurance verification: SoonerCare covers detox and residential SUD services with prior authorization 11. The facility should handle this verification process, not you.
- Polysubstance awareness: If you use other substances like benzodiazepines, alcohol, or stimulants alongside opioids, the intake process must address all substances to ensure a safe and comprehensive detox plan.
If You’re Reading This for Someone You Love
If you are a family member or friend supporting someone struggling with opioid use, you’ve likely experienced significant challenges. While you cannot force someone into detox, you can help remove barriers to seeking help. Call a facility yourself to inquire about SoonerCare or private insurance coverage; detox and residential substance use services are covered benefits, with prior authorization handled by the facility 11. Also, ask about the post-detox plan, as detox without a bridge to ongoing Medication-Assisted Treatment (MAT) is not complete treatment 6.
Offer the phone number and information without judgment. Your informed and supportive approach can be the catalyst for them to make that crucial call.
A Direct Next Step
Taking the first step, even if it’s just making a phone call, is significant. You don’t need to be ready to quit forever to explore your options.
A simple next step is to call a medically supervised detox facility in Oklahoma City and ask two key questions: “What medications do you use for opioid withdrawal?” and “What does the bridge to ongoing care look like after 72 hours?” If the answers include buprenorphine, methadone, or naltrexone 4, and a clear, written plan for post-detox care 6, you are likely speaking with a legitimate program.
If cost is a concern, ask them to verify your SoonerCare or private insurance benefits during the call 11. If you are in crisis, call 988. Renewal Springs Detox is one option in the OKC metro. Any call you make today towards seeking help is a positive step.
Speak With a Medical Detox Expert Now
Get immediate answers from a licensed professional about safe, medication-assisted detox options in Oklahoma City.

Frequently Asked Questions
Does SoonerCare cover medication-assisted detox in Oklahoma City?
Yes, SoonerCare covers detox and residential substance use disorder services for eligible individuals, including children and adults, with prior authorization 11. Outpatient services are also covered. The detox facility typically handles the prior authorization process during intake.
How long does medically supervised opioid detox take?
Acute opioid withdrawal, with medication support, generally lasts three to seven days. The exact duration depends on the substances used, dosage, and any co-occurring substance use. Detox is an initial phase; ASAM clarifies that withdrawal management alone is not a complete treatment for opioid use disorder 6. A plan for ongoing care is initiated before discharge.
Is buprenorphine or methadone just replacing one addiction with another?
No. These medications activate opioid receptors in a controlled manner, providing stable levels without producing a high. SAMHSA recognizes their effectiveness in reducing opioid use, preventing overdose deaths, and improving recovery outcomes 8. When managed by a clinician, these medications are considered medical treatment, not a substitute addiction.
What’s the difference between detox and treatment for opioid use disorder?
Detox focuses on managing acute withdrawal symptoms, typically over 72 hours, through medication and monitoring. Treatment, however, encompasses the long-term process that follows detox, including continued Medication-Assisted Treatment (MAT) with buprenorphine, methadone, or naltrexone, alongside counseling and recovery support. ASAM explicitly states that detox alone is insufficient for treating opioid use disorder 6; the transition to ongoing care is where sustained recovery is built.
Is rapid or ultra-rapid detox a safe option?
No. ASAM’s National Practice Guideline advises against ultra-rapid opioid detoxification due to a high risk of severe adverse events, including death 6. Programs promoting quick-fix or anesthesia-assisted detox should be viewed with caution. Safe withdrawal management prioritizes patient safety and is paced according to the body’s ability to adjust.
What happens if I’ve been using fentanyl before I come in?
It is crucial to be honest with the intake team about your fentanyl use, including dosage, frequency, and last use. Fentanyl’s unique pharmacokinetics can affect the timing of buprenorphine induction. Medical staff will use the Clinical Opiate Withdrawal Scale to determine the appropriate time to administer buprenorphine, typically when your score reaches 11 or higher, to prevent precipitated withdrawal 13. Your honesty ensures a safer detox process.
References
- Data – Oklahoma.gov (Drug Overdose Data). https://oklahoma.gov/health/health-education/injury-prevention-service/drug-overdose/data.html
- Drug Overdose Deaths, 2019-2023 – Oklahoma (IPS Fact Sheet). https://oklahoma.gov/content/dam/ok/en/health/health2/aem-documents/prevention-and-preparedness/injury-prevention/drug-overdose/2025%20State%20Drug%20OD%20-%20IPS%20-%20Fact%20Sheet.pdf
- Drug Overdose Data Dashboard – Oklahoma.gov. https://oklahoma.gov/health/health-education/injury-prevention-service/drug-overdose/data/drug-overdose-data-dashboard.html
- TIP 63: Medications for Opioid Use Disorder. https://library.samhsa.gov/product/tip-63-medications-opioid-use-disorder/pep21-02-01-002
- Medications for Opioid Use Disorder: For Healthcare and Addiction Professionals, Policymakers, Patients, and Families. https://pubmed.ncbi.nlm.nih.gov/30566313/
- The ASAM National Practice Guideline for the Treatment of Opioid Use Disorder (Full Guideline PDF). https://www.dhcs.ca.gov/wp-content/uploads/2025/10/ASAM2B20202BOUD.pdf
- Medication-Assisted Treatment of Opioid Use Disorder (Clinical Guidance). https://www.azahcccs.gov/PlansProviders/TargetedInvestments/Downloads/MEDICATION-ASSISTED_TREATMENT_OF%20OPIOID_USE_DISORDER.pdf
- Dear Colleague Letter: Guidance for Evidence-Based Medication Treatment for Opioid Use Disorder (MAT/MOUD). https://www.samhsa.gov/sites/default/files/dear-colleague-letter-mat-moud-guidance.pdf
- Federal Guidelines for Opioid Treatment Programs (2024). https://library.samhsa.gov/product/federal-guidelines-opioid-treatment-programs-2024/pep24-02-011
- Drug Overdose Mortality: Stats of the States. https://www.cdc.gov/nchs/state-stats/deaths/drug-overdose.html
- Mental Health and Substance Abuse Services – Oklahoma Health Care Authority. https://oklahoma.gov/ohca/individuals/programs/mental-health-and-substance-abuse-services.html
- Mental Health Services | City of Oklahoma City. https://www.okc.gov/Services/Public-Safety/Mental-Health-Services
- Medication Assisted Treatment for Opioid Use Disorder (Federal Bureau of Prisons Clinical Guidance). https://www.bop.gov/resources/pdfs/opioid_use_disorder_cg.pdf
- Opioids in Oklahoma (ODMHSAS Report). https://oklahoma.gov/content/dam/ok/en/odmhsas/documents/prevention/steow/opioids-in-oklahoma-final.pdf
- Contact Us – Oklahoma Department of Mental Health and Substance Abuse Services. https://oklahoma.gov/odmhsas/contact-us.html


